Personalized Medical Care & Dedicated International Patient Concierge

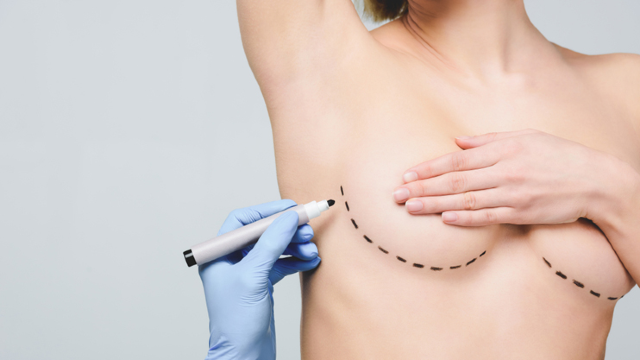
Medical Guide
Endoscopic Breast Augmentation: Where the Scar Can Go
A camera in the pocket changes which incision is workable, and the incision decides where the mark ends up. That is the real content of this comparison.
Schedule a ConsultationEndoscopic Breast Augmentation: Where the Scar Can Go
Medically reviewed by Dr. Hong Sung Taek, Chief Director, Merry Plastic Surgery
The comparison people expect from this title is about how invasive each approach is. The comparison that actually matters is about sight lines.
An implant sits in a pocket that has to be made. Making it well means seeing the space you are dissecting — the tissue planes, the vessels, the boundaries of the pocket. From an incision close to the pocket, you can see it directly. From an incision far away, you cannot.
That is what the endoscope changes. A high-definition camera passed down to the working area supplies the view that distance took away, which makes a distant incision workable — and a distant incision is one that does not sit on the breast.
Everything else in this comparison follows from that.
What Merry Plastic Surgery publishes
The technique. A breast augmentation using a high-definition endoscopic camera to provide magnified visualization during implant-pocket creation and tissue dissection, paired with dual-plane implant placement and individualized incision selection based on breast tissue, chest anatomy and aesthetic goals.
The scar claim, stated exactly. The axillary incision option can keep the scar away from the breast itself, which the record says may be particularly relevant to patients who prefer breast skin without an incision scar.
The purpose of the visualization. The published claims say magnified, high-resolution visualization during pocket creation is intended to support controlled tissue dissection and reduce unnecessary tissue trauma and bleeding.
The implants. Mentor silicone gel implants are used.
Anesthesia. General. The endoscopic technique is described as intended to reduce unnecessary tissue trauma and bleeding during dissection, which the clinic associates with less postoperative pain and a comparatively shorter recovery period. Individual pain and recovery experiences vary.
Duration. Approximately one to two hours. Hospitalization is not required according to the supplied clinic information, and eligible patients return home the same day.
Recovery. Adhesive wound closures typically removed after approximately one week, with two to three follow-up visits. General recovery allowing a return to most daily activities typically expected within one to two weeks, varying by individual and approach.
The incision question, honestly framed
Breast augmentation incisions are placed in one of a few general locations, and the trade is always the same: proximity to the pocket against where the mark ends up.
An incision at the fold beneath the breast is close to the work. An incision in the armpit is not — it requires dissecting a considerable distance to reach and create the pocket, and doing that without adequate visualization is the reason the axillary approach is technically demanding.
The endoscope addresses the visualization half of that problem. It does not abolish the distance; it makes the distance workable by supplying magnified sight where direct sight is unavailable.
So the published claim is precise and worth repeating as written: the axillary option can keep the scar away from the breast itself. Not that there is no scar. Not that the scar is invisible. That its location can be moved off the breast.
The National Library of Medicine's overview of scars covers how any incision matures, which is individual and is not determined by the approach.
What "dual-plane" adds
The published technique pairs endoscopic visualization with dual-plane implant placement, and the claims add that dual-plane placement can be adapted to different breast-tissue types.
The short version of what that means: implants can sit in different positions relative to the chest muscle and the breast tissue, and a dual-plane approach positions them in a way that relates to both rather than committing entirely to one. The adaptability is the point — the published language is about matching the placement to tissue type rather than applying one plane to everyone.
That connects to the consultation, which is published in unusual detail for this clinic: it reviews aesthetic goals, breast and chest-wall anatomy, existing breast tissue, breast position, activity level, medical history and any previous breast surgery, and then uses diagnostic and precision analysis to assess chest dimensions and tissue characteristics and help determine implant type, size, profile, placement plane and incision.
Five decisions, made together. Activity level appearing on that list is worth noticing — it is not an aesthetic variable, and it belongs in the conversation if you train, lift, swim or play a sport seriously.
Who the record describes
Individuals with underdeveloped or flat-looking breasts; loss of breast volume after weight reduction or childbirth and breastfeeding; a relatively prominent chest muscle; breast asymmetry; or a wish for fuller breasts with a proportionate, natural-looking result.
The published reasons patients choose this approach name increased volume and improved proportion while prioritizing natural-looking contours and minimal visible scarring.
Who is unsuitable is left unconfirmed in the published record, so suitability is a consultation question rather than a page one.
The risk list, read carefully
Six items are published, and each is standard in implant surgery rather than specific to the endoscopic route:
Infection. Infection control and antibiotics cover the general picture.
Changes in nipple sensation.
Breast asymmetry.
Capsular contracture — named again separately as a possible long-term concern.
Implant rippling or palpability.
Other implant- or surgery-related complications, with individual risks to be reviewed during informed consent.
Two observations.
Capsular contracture is mentioned twice. Once in the list and once as a long-term concern in its own right. That repetition is the record telling you it is not a footnote. The body forms a capsule around any implant; when that capsule tightens, shape and comfort change. It can happen years later.
The endoscopic technique is not claimed to change this list. The published benefit of the visualization is controlled dissection and reduced unnecessary trauma and bleeding — a statement about the operation, not about long-term implant behavior. A page claiming the endoscopic route reduces capsular contracture is claiming something this record does not.
The National Library of Medicine's overview of breast diseases covers the surrounding territory, and immune system and disorders the general biology of a foreign-body response.
The sentence that should shape your planning
"Breast implants are not considered lifetime devices, so ongoing monitoring and periodic follow-up are recommended."
That is published, and it is the most consequential line in the whole record for someone choosing this operation abroad.
It means the relationship does not end at the last follow-up visit. Implants require monitoring over years, and if you live on another continent, that monitoring will be done by somebody else.
Three practical consequences.
Ask what monitoring is recommended and on what schedule, so you can arrange it at home.
Get your implant documentation in writing — type, size, profile, placement plane, incision, date, and the manufacturer's details. A clinician at home cannot look up an operation performed in Seoul. Personal health records covers how to keep it.
Identify a local clinician before you travel, not after something prompts the search. The CDC's guidance on medical tourism and on what to do when sick abroad makes continuity of care the recurring theme, and it applies most strongly to implants.
Recovery and the trip
Same-day surgery for eligible patients. Adhesive closures off at about a week. Two to three follow-up visits. General recovery to most daily activities in one to two weeks.
The follow-up count is the planning number, and those appointments have to fit a clinic week that runs 9:30 a.m. to 6:30 p.m. Monday through Friday and 9:30 a.m. to 4:00 p.m. on Saturday, closed Sundays and public holidays.
Flying after surgery is a question for the surgical team rather than a general rule — the CDC covers air travel considerations, and travelers' health the wider preparation. Confirm the recommended stay before booking.
Five questions for the consultation
Which incision would you recommend for me, and why that one? The answer connects anatomy to scar location.
Which plane, and what does my tissue type argue for? Dual-plane is published as adaptable; ask what it is being adapted to.
How does my activity level affect the plan? It is on the published assessment list.
What monitoring do you recommend, and at what intervals? Because implants are not lifetime devices.
What documentation will I leave with? Ask before surgery, not at discharge.
Send them ahead through the clinic's contact page. What the clinic says about its own approach is published on its about page.
What the record does not compare
Worth saying plainly: Merry Plastic Surgery publishes its endoscopic technique and does not publish a traditional open augmentation alongside it for comparison.
So the contrast drawn in this article is between an endoscopic approach as published and open technique as a general category — not between two services offered here. Anyone quoting side-by-side recovery figures for "traditional" augmentation at this clinic is quoting something the record does not contain.
The practical consequence is a narrower question than the title suggests: not "which technique should I choose here?" but "given my anatomy and goals, which incision and which plane does the published technique call for?" That is the decision that exists, and it is the one the published consultation is built to make.
The Bottom Line
- The endoscope solves a sight-line problem, which is what makes a distant incision workable — and a distant incision is one that can sit off the breast.
- The published claim is exact: the axillary incision option can keep the scar away from the breast itself. It is about location, not absence.
- Visualization is described as intended to support controlled dissection and reduce unnecessary trauma and bleeding — a claim about the operation, not about long-term implant behavior.
- Capsular contracture appears twice in the published record, including as a long-term concern. The technique is not claimed to change that.
- Implants are not lifetime devices, so arrange monitoring at home, keep your implant documentation, and identify a local clinician before you travel.
Frequently Asked Questions
What does the endoscope do?
It provides magnified, high-definition visualization during implant-pocket creation and tissue dissection, supplying sight where an incision placed at a distance from the pocket would otherwise limit it.
Does it mean no scar?
No. The published claim is that the axillary incision option can keep the scar away from the breast itself — a statement about where the mark sits, not whether there is one.
What is dual-plane placement?
An implant position related to both the chest muscle and the breast tissue rather than committing entirely to one, described as adaptable to different breast-tissue types.
How long does the surgery take?
Approximately one to two hours under general anesthesia, with no hospitalization required and same-day discharge for eligible patients.
What is the recovery?
Adhesive wound closures typically removed at about one week, two to three follow-up visits, and general recovery to most daily activities usually within one to two weeks.
What are the published risks?
Infection, changes in nipple sensation, breast asymmetry, capsular contracture, implant rippling or palpability, and other implant- or surgery-related complications.
Does the endoscopic technique reduce capsular contracture?
The published record does not claim that. Its stated benefit is controlled dissection with reduced unnecessary tissue trauma and bleeding.
Do implants need long-term follow-up?
Yes. The record states that implants are not considered lifetime devices and that ongoing monitoring and periodic follow-up are recommended.
This article is for general informational purposes and does not constitute individualized medical advice. It is not a self-diagnosis tool. Surgical results vary with anatomy, tissue condition and individual healing, and whether a procedure is appropriate for you can only be determined through an in-person consultation and examination by a qualified plastic surgeon.
More Articles
Continue reading our clinical guides.
Operating Room Standards: What You Can Ask and Verify
You will never inspect a sterilization room. What you can do is ask questions whose answers reveal whether a facility thinks about this systematically.
Learn More
Staying in Korea After Rhinoplasty: Why No Number Exists
The clinic publishes no fixed figure, and that is not an omission. A nose heals on a timetable long enough that any single number would be misleading.
Learn More

Bringing Someone With You: What a Companion Actually Does
Decide this by listing the hours a companion would actually cover, rather than by how you feel about going alone. Most are ordinary, and a few are not.
Learn More